
Choosing the right Surgical Retractors and Spreaders affects exposure, tissue protection, fatigue, and procedural control. The decision is rarely solved by selecting the largest blade. It requires matching instrument geometry, pressure distribution, access depth, and surgical specialty.
Grand View Research reports continued growth in the global surgical instruments market, driven by minimally invasive procedures, aging populations, and technology upgrades. Fortune Business Insights also identifies increasing procedure volumes as a major market factor. These figures show demand, not guaranteed clinical value. A growing market can still contain poor-fitting designs.
Richard Satava, MD, a recognized surgical-technology researcher, offers a useful principle: “Technology should serve the surgeon, not distract the surgeon.” That idea belongs at the center of this guide. A retractor should hold exposure steadily, without crushing tissue or obstructing visualization. A spreader should provide controlled separation, not forceful opening that transfers pressure to delicate structures.
The following seven tips examine blade shape, working depth, handle design, locking systems, radiolucency, sterilization, and ergonomic control. Look closely at the details. A narrow blade may improve access between ribs, while a broader surface may reduce pressure on soft tissue. Small differences matter.
There is no universal best instrument. That assumption deserves scrutiny. Surgeon experience, anatomy, case duration, and facility protocols can change the choice. Reliable selection also requires reviewing manufacturer specifications, validated cleaning instructions, and evidence from recognized surgical organizations. When practical testing is possible, compare grip comfort, visibility, stability, and tissue contact under realistic operating conditions.
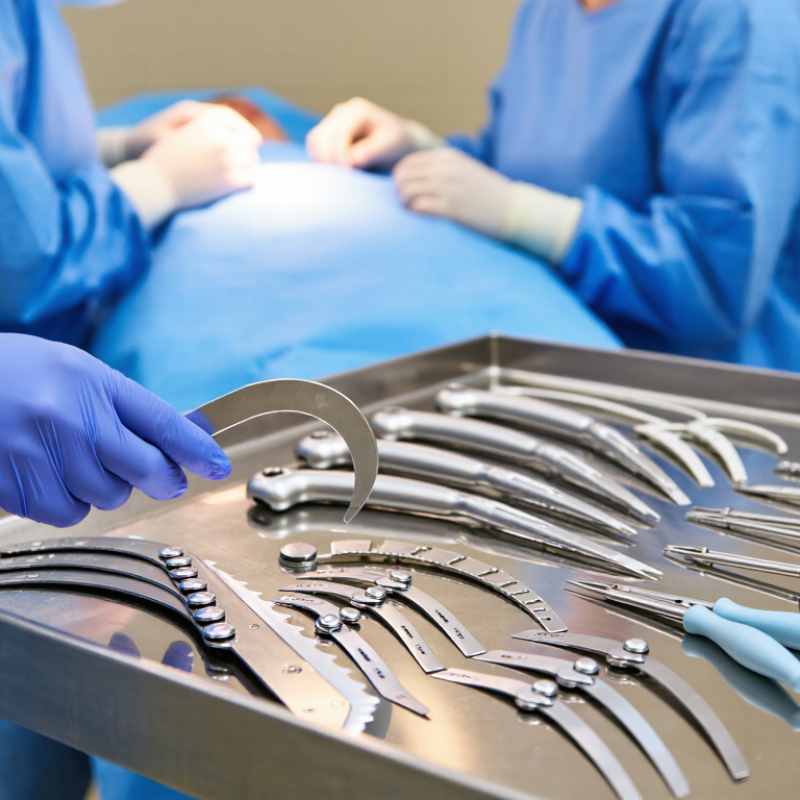
Selecting a retractor begins with the anatomy, not the instrument drawer. Handheld retractors suit brief exposure changes and allow an assistant to adjust pressure immediately. Self-retaining retractors maintain a steady field during longer procedures. They can reduce assistant fatigue, but excessive tension may remain unnoticed.
Match the design to the surgical site. Abdominal procedures often require broad, atraumatic blades, while orthopedic exposure may need stronger bone spreaders. Rib spreaders must provide controlled separation without concentrating force on fragile structures. Narrow blades help reach deep spaces, but they can create pressure points. Check blade curvature, working depth, visibility, and tissue contact. A larger opening is not automatically better.
Seven practical checks include exposure tissue sensitivity depth force control stability ergonomics and cleaning requirements. Ratcheted mechanisms should lock securely and release smoothly. Handles must remain comfortable with gloved hands. The instrument should not obstruct lighting, imaging, or nearby anatomy. Radiolucent components may help when intraoperative imaging is required. Always compare the device with the procedure’s positioning and access plan. In practice, teams sometimes choose familiar instruments too quickly. That habit deserves review. Manufacturer instructions, sterilization protocols, and local surgical policy remain essential before use.
Choosing a retractor starts with anatomy, not catalog dimensions. Measure incision depth, tissue thickness, and the working angle. A broad blade may protect skin but obstruct a narrow cavity. A slim blade may improve access but concentrate pressure. Match blade curvature to the tissue plane. Match handle length to the surgeon’s reach. Keep the instrument stable without excessive force. Small differences matter.
In practice, I would check the patient’s body habitus and the planned surgical position before selecting size. Deep pelvic work often needs longer shafts and narrower profiles. Superficial procedures usually benefit from shorter, lighter instruments. Blunt edges can reduce accidental tissue catching. However, “atraumatic” is not automatic. Excessive blade pressure can still impair local perfusion. That point deserves more attention during team review.
The World Health Organization’s 2016 Global Guidelines report an 11% surgical-site infection incidence in low- and middle-income countries. This figure does not prove that retractors cause infection, but it reinforces careful tissue handling and disciplined wound protection. CDC NHSN surveillance reports also use procedure-specific infection rates, showing why one universal retractor size is unreliable. Instrument choice should reflect the operative site, not habit. I would document the reason for unusual dimensions, then reassess exposure during surgery. Perfect selection is rarely possible. Careful adjustment remains part of safe technique.
A safe instrument begins with its material, not its appearance. Stainless steel offers strength, corrosion resistance, and predictable cleaning performance. Polymer components can reduce weight and contact pressure, but they need careful inspection for cracks or surface changes. Titanium may improve handling when weight matters, although its cost can complicate standardization. Ask whether the material tolerates the intended sterilization cycle. Do not assume every metal behaves alike.
Visibility depends on more than a polished surface. Check the working tip under strong, angled light. A mirror-like finish may create glare, while a matte finish can hide scratches or residue. Choose a design that keeps the operative field open without blocking the team’s line of sight. Handle shape also matters during long procedures. It should support controlled movement, not force the wrist into an awkward angle. Small differences become obvious after an hour.
Tissue protection deserves the closest review. Rounded edges, atraumatic teeth, and smooth transitions can reduce crushing and sliding. Match the spreader’s width and force range to the tissue’s size and fragility. Confirm that locking mechanisms release easily and do not require sudden pressure. Inspect joints for looseness before use. A checklist helps, but it is not perfect. Record recurring issues and revise the selection process with surgical and sterile-processing staff. That feedback is practical evidence, not paperwork.
7 Tips for Choosing Surgical Retractors and Spreaders
Assessing Ergonomics, Handling, and Surgical Access
Choosing a retractor begins with the surgeon’s working posture, not the instrument tray. A 2020 systematic review in the International Journal of Surgery found musculoskeletal symptoms among surgeons ranging from 44% to 95%. That range is uncomfortable, but useful. It shows why handle design and sustained force deserve attention. Check whether the grip supports a neutral wrist during a simulated procedure. Fit matters. Avoid handles that press sharply into the palm or require constant finger tension. The National Institute for Occupational Safety and Health links awkward posture, force, and repetition with work-related musculoskeletal risk.
Test under load. Ask staff to hold the retractor for several minutes, then assess wrist angle, shoulder elevation, and visibility. A light instrument can still feel unstable. A heavier one may reduce repositioning. The correct choice depends on access, tissue depth, and fatigue. Select tips that provide stable exposure without excessive pressure. Confirm that locking mechanisms can be adjusted with gloved hands. Check whether the frame blocks suction, lighting, or adjacent instruments. Small details matter. AORN guidance on perioperative ergonomics supports evaluating equipment within the actual workflow, rather than judging it on a display table. I have found that demonstrations often look easier than real cases. That is a limitation worth admitting. Record user feedback after procedures, including slips, hand strain, and difficult adjustments, then revise the selection criteria.
| No. | Selection Tip | What to Assess | Practical Evaluation | Preferred Characteristics | Warning Signs |
|---|---|---|---|---|---|
| 1 | Match the Instrument to the Surgical Approach | Blade shape, working length, retractor depth, and the amount of exposure required for the intended procedure. | Review the operative approach and compare the instrument with the expected incision, cavity depth, tissue thickness, and target anatomy. | Adequate reach without excessive shaft length; blade geometry that provides exposure while avoiding unnecessary tissue displacement. | The instrument cannot reach the target, obstructs the field, or requires excessive force to maintain exposure. |
| 2 | Prioritize Handle Ergonomics | Grip diameter, surface texture, handle contour, finger clearance, and compatibility with gloved hands. | Hold and operate the retractor with surgical gloves. Check whether the wrist remains neutral and whether the controls can be reached without changing grip. | Secure, non-slip handling; rounded edges; balanced grip; and controls that can be adjusted with minimal hand repositioning. | Sharp edges, slippery surfaces, excessive grip force, or wrist bending during routine use. |
| 3 | Check Weight and Balance | Total instrument mass, center of gravity, balance during deployment, and the force needed to hold or adjust the device. | Test the instrument in the intended position for several minutes and assess fatigue, drift, and the need for assistance from another staff member. | Stable positioning with low perceived hand and wrist strain; weight distributed toward the support point rather than the distal blade. | The tool feels front-heavy, shifts unexpectedly, or causes noticeable fatigue during simulated use. |
| 4 | Evaluate Adjustment and Locking Control | Opening range, adjustment increments, locking mechanism, release action, and stability under sustained load. | Open, position, lock, release, and reposition the spreader using gloved hands. Confirm that the mechanism remains stable without sudden movement. | Smooth, predictable adjustment; positive locking feedback; controlled release; and no unintended closing or slipping. | Stiff or jerky movement, difficult release, unclear locking status, or unintentional position changes. |
| 5 | Protect the Surgical Field | Blade profile, tip design, contact area, atraumatic edges, visibility around the instrument, and potential pressure points. | Inspect the working end and confirm that the blade provides exposure without blocking visualization or creating concentrated pressure on tissue. | Smooth, atraumatic contact surfaces; appropriate blade width; rounded or protected edges where clinically suitable; and clear visualization. | Burrs, sharp unintended edges, unstable tips, excessive pressure concentration, or poor visibility of the operative site. |
| 6 | Confirm Access and Instrument Compatibility | Line of sight, instrument clearance, compatibility with lights and suction, and the ability to introduce or remove other instruments. | Simulate the operative setup with adjacent instruments in place. Check whether the retractor interferes with suturing, visualization, suction, or electrosurgical equipment. | Provides stable exposure while leaving sufficient working room for the surgeon and assistant. | Crowded access, blocked visualization, difficult instrument exchange, or frequent repositioning during the procedure. |
| 7 | Review Cleaning, Sterilization, and Maintenance | Disassembly requirements, joints and hinges, cleanability, material compatibility, inspection access, and sterilization instructions. | Compare the design with the facility’s validated cleaning and sterilization process. Inspect moving parts for retained soil, corrosion, or wear after repeated processing. | Accessible surfaces, minimal soil-retaining crevices, clear reprocessing instructions, corrosion-resistant construction, and replaceable or serviceable components where applicable. | Complex inaccessible joints, unclear reprocessing guidance, corrosion, loose components, or inconsistent locking performance. |
Choosing surgical retractors and spreaders requires more than checking their shape or opening range. Sterilization performance deserves close attention. Confirm that the instrument tolerates the facility’s validated cleaning and sterilization cycle. Steam exposure, temperature, and drying time can affect different materials in different ways. Inspect joints, serrations, and locking mechanisms after every cycle. Tiny residue can remain in hidden gaps.
Durability also depends on design details. A stable frame should open smoothly without excessive force. Handles must feel secure, even when gloves are wet. Look for smooth surfaces without pits, scratches, or flaking finishes. These defects may trap soil and complicate cleaning. In practice, a heavier instrument is not always stronger. It may simply increase hand fatigue during a long procedure. I have found that balance matters as much as thickness.
Maintenance instructions should be specific, practical, and easy for staff to follow. Rinse instruments promptly after use, because dried tissue becomes harder to remove. Use only cleaning agents approved for the instrument’s materials. Lubricate moving points when the instructions permit it. Do not force a stiff hinge. That can hide a developing fault. Keep inspection records, including damage, repairs, and failed cleaning checks. Staff feedback is valuable, although it can be inconsistent. A short trial in the operating environment may reveal awkward handling that specifications miss.
Begin with the anatomy, not the instrument drawer. Assess incision depth, tissue thickness, working angle, and tissue sensitivity. Small differences matter.
Handheld retractors suit short exposure changes. An assistant can adjust pressure immediately. This flexibility may improve control during changing surgical views.
Self-retaining retractors help maintain exposure during longer procedures. They may reduce assistant fatigue. However, unnoticed tension can remain too high.
Broad blades may protect superficial tissue but obstruct narrow cavities. Slim blades improve deep access but can create pressure points. Match curvature to the tissue plane.
Deep pelvic work often needs longer shafts and narrower profiles. Check visibility and handle reach. A small adjustment may improve access.
Use controlled force and reassess tissue appearance regularly. Blunt edges can reduce tissue catching. “Atraumatic” does not guarantee safe pressure.
The mechanism should lock securely and release smoothly. Test it before use. A difficult release deserves attention.
Compare the retractor with the planned position and access route. It should not block lighting, imaging, or nearby anatomy. Radiolucent parts may help during imaging.
Follow the manufacturer’s instructions, sterilization process, and local surgical policy. Inspect hinges, teeth, blades, and handles. Familiar instruments are not automatically suitable.
No. Body habitus, operative site, tissue thickness, and access angle all differ. A perfect selection is unlikely. Document unusual choices and reassess exposure during surgery.
Choosing the right Surgical Retractors and Spreaders is essential for maintaining a clear, stable, and safe operative field. Begin by understanding the differences between handheld, self-retaining, fixed, and spreading instruments, then match each type to the procedure and anatomical area involved. The instrument’s size, length, curve, and blade shape should provide adequate exposure without applying unnecessary pressure to surrounding tissues. Material selection also matters: durable, corrosion-resistant construction and a suitable surface finish can support long-term performance, while design features that improve visibility help surgeons work with greater precision.
Ergonomics should be evaluated carefully, including grip comfort, balance, controllable tension, and ease of repositioning. A well-designed instrument can improve access while reducing hand fatigue and tissue strain. Before purchase, confirm that the retractors and spreaders are compatible with required sterilization methods, easy to inspect and clean, and resistant to repeated use. Routine maintenance, proper handling, and timely inspection will help preserve functionality, reliability, and patient safety throughout their service life.
